Learn about our physician preference medical and surgical supplies
Learn about our commitment to supporting health systems through quality medical supplies and robust supply chain strategies
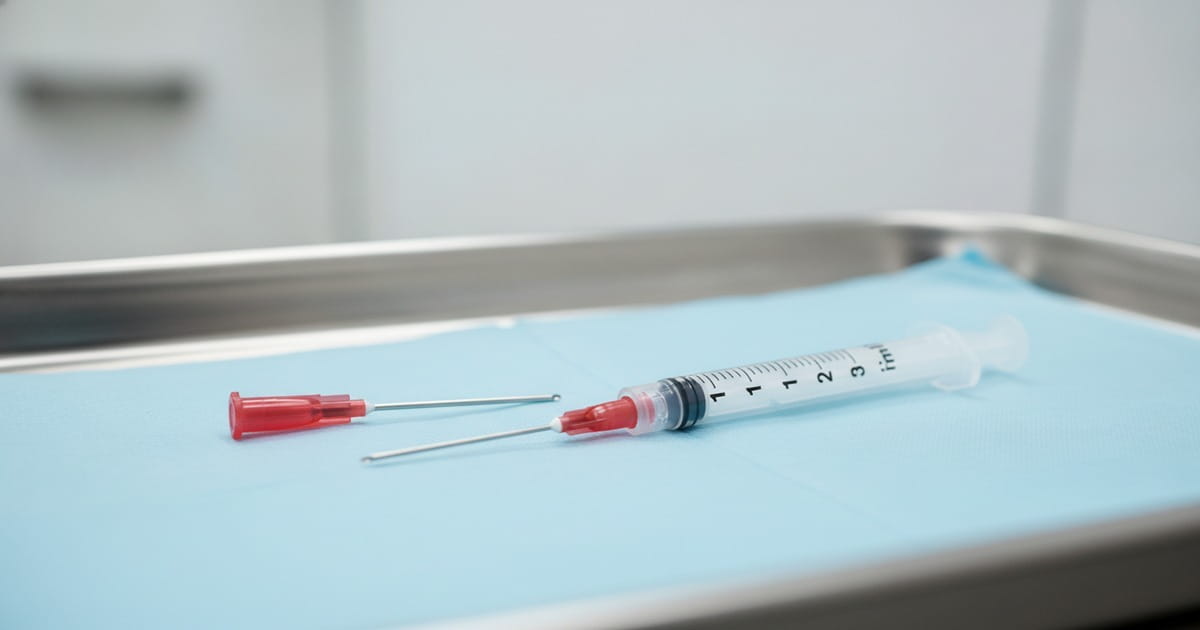
Most injectable doses begin the same way: a needle goes into a vial or ampule, medication is drawn into a syringe, and the preparation moves to the patient. That first step happens millions of times a day in U.S. hospitals, and in many facilities it is still performed with a conventional sharp needle, even though the drawing-up step never touches a patient. Blunt fill needles exist to remove that unnecessary sharp from the workflow. This guide covers what blunt fill needles are, when a filter version is the better choice, and how to select gauge and length for your medication preparation areas.
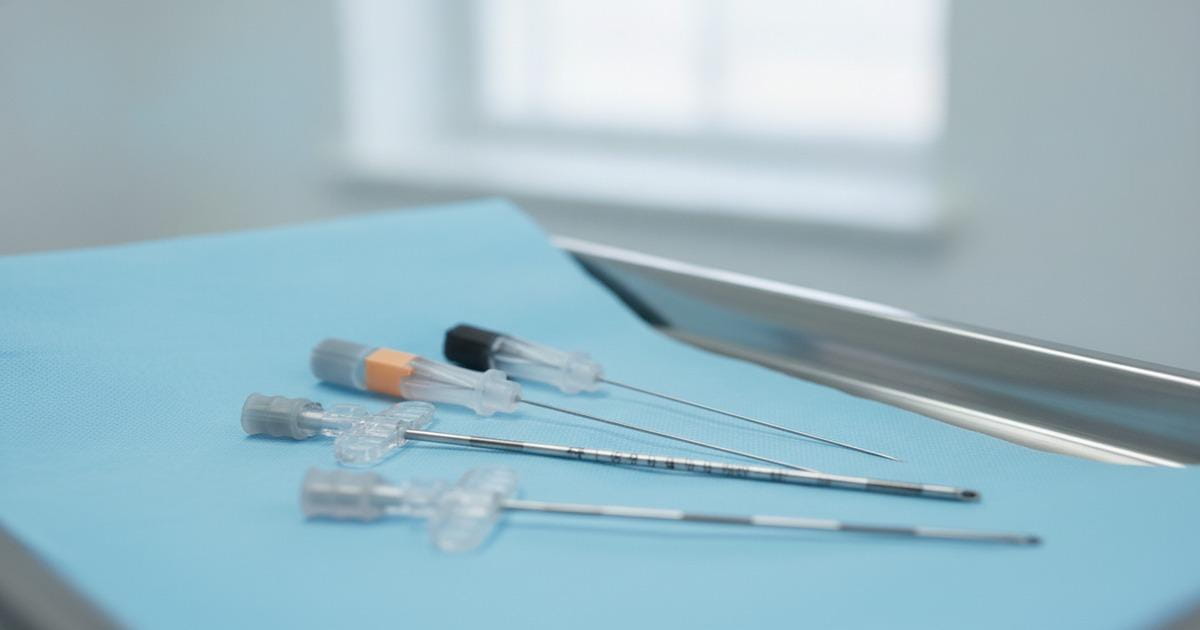
Few device choices in anesthesia and diagnostic medicine carry as much day-to-day consequence as the spinal needle. Tip geometry and gauge influence how easily the needle is placed, how clearly cerebrospinal fluid (CSF) confirms position, and how likely the patient is to develop a post-dural puncture headache (PDPH) — a complication that can extend a hospital stay or bring a discharged patient back through the door.
Few facilities convert to safety-engineered devices overnight. Contracts expire on different dates, departments carry different budgets, backorders arrive out of sequence, and some procedures keep conventional devices longer than others. The predictable result is a mixed fleet — conventional and safety-engineered devices in use at the same time, sometimes on the same unit and occasionally in the same supply drawer.
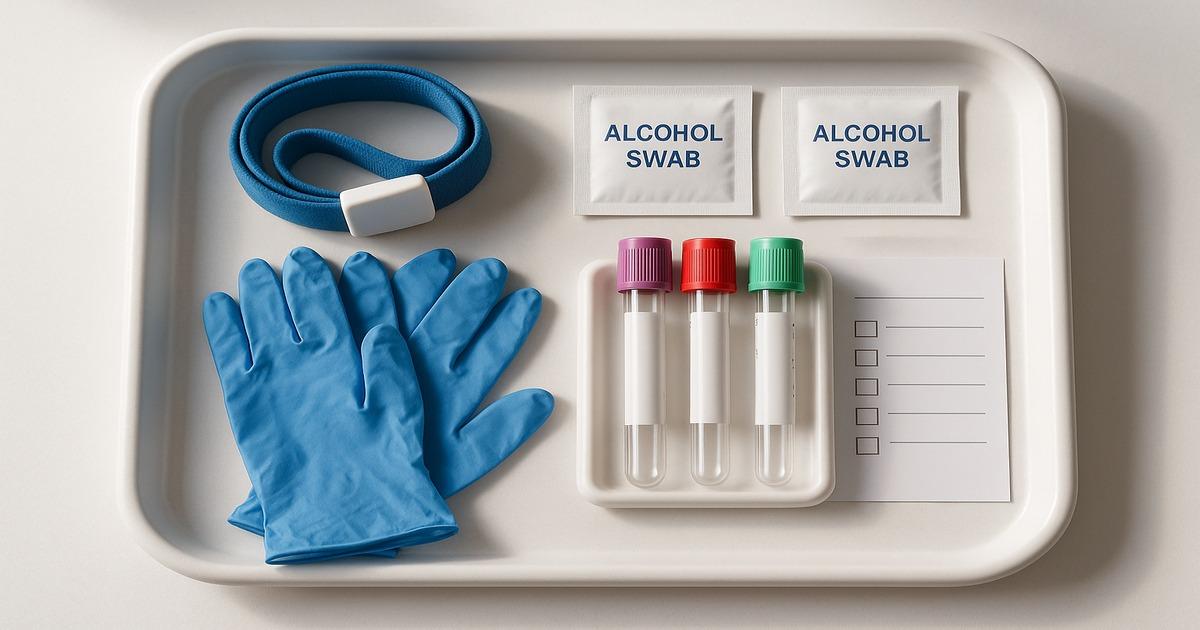
A mislabeled tube or a draw performed out of sequence rarely looks dramatic in the moment — but it can mean a rejected specimen, a redraw, or a result that quietly steers a clinical decision the wrong way. For nurses, phlebotomists, and lab staff, knowing which tube to use, in what order, and why, is one of the highest-leverage skills in the preanalytical phase.
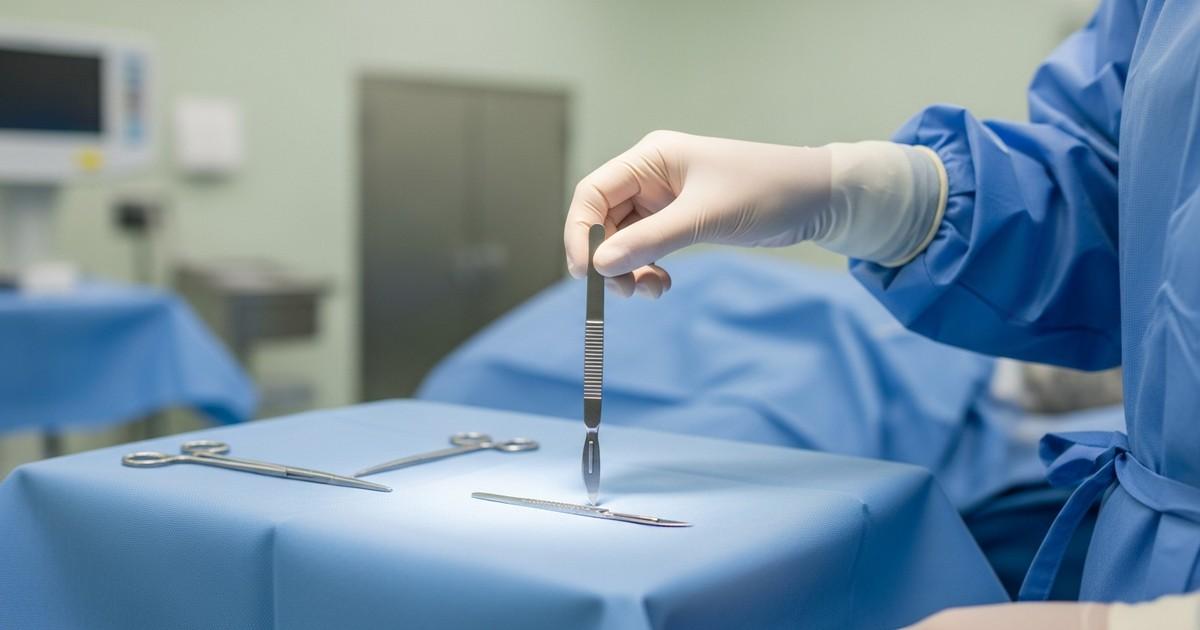
In operating rooms and sterile processing departments, scalpels are among the most hazardous instruments to handle — not during incision, but during passing, blade removal, and disposal. According to Exposure Prevention Information Network (EPINet) data summarized by the CDC, scalpel blades account for approximately 6–8% of all sharps injuries across hospital settings — and a 2023 report from the National Institute for Occupational Safety and Health (NIOSH) found that OR sharps injuries actually increased over time, even as nonsurgical sharps injuries declined. The problem is not technology — it is training, workflow, and compliance.
Most phlebotomy training happens during orientation — a few intense days of instruction followed by months of on-the-job practice with minimal structured feedback. The result: bad habits calcify. Needle angles drift. Flashback checks get rushed. Tube order gets fuzzy under pressure.
Safety scalpels have become a standard recommendation across surgical and procedural settings — and for good reason. They reduce the risk of sharps injuries, support OSHA Bloodborne Pathogens Standard compliance, and reduce cross-contamination risks associated with reusable handles. But despite clear safety advantages, adoption remains uneven across healthcare facilities.
Most laboratory directors and phlebotomy supervisors think about hemolysis and redraws in clinical terms — compromised specimens, delayed results, frustrated patients. Finance teams think in dollars. Bridging that language gap is how you get budget approval for better equipment, standardized workflows, and sharps safety upgrades. This post gives you a straightforward total cost of ownership (TCO) framework that translates everyday phlebotomy inefficiencies into the numbers a Chief Financial Officer (CFO) will actually read.
Demand for off-site blood collection is climbing on every front. Hospital-at-home programs, Medicare Advantage in-home assessments, employer wellness draws, clinical trial home visits, skilled nursing facility (SNF) routes, and concierge laboratory services are all pushing more specimens out of fixed draw stations and into living rooms, conference rooms, and parked vans. The Centers for Medicare & Medicaid Services (CMS) Acute Hospital Care at Home waiver, extended again in recent reauthorizations, has made the model permanent enough for serious capital investment.