Learn about our physician preference medical and surgical supplies
Learn about our commitment to supporting health systems through quality medical supplies and robust supply chain strategies
A mislabeled tube is not a paperwork mistake. It is a direct line to the wrong transfusion, the wrong diagnosis, a delayed treatment, or a sentinel event. The College of American Pathologists (CAP) Q-Tracks studies have consistently shown specimen identification errors affecting roughly 1 in every 1,000 specimens across participating laboratories—a rate that sounds small until you multiply it across the millions of tubes drawn every day.
Hemolysis—the breakdown of red blood cells that releases intracellular contents into serum or plasma—is the leading cause of specimen rejection in clinical laboratories. Studies consistently put hemolysis-related rejection rates between 40% and 70% of all preanalytical errors, translating to redraws, delayed results, increased sharps waste, and patient dissatisfaction. For a mid-size hospital running 500 blood draws per day, even a 5% hemolysis rate means 25 redraws daily—thousands of unnecessary needle sticks and lab hours annually.
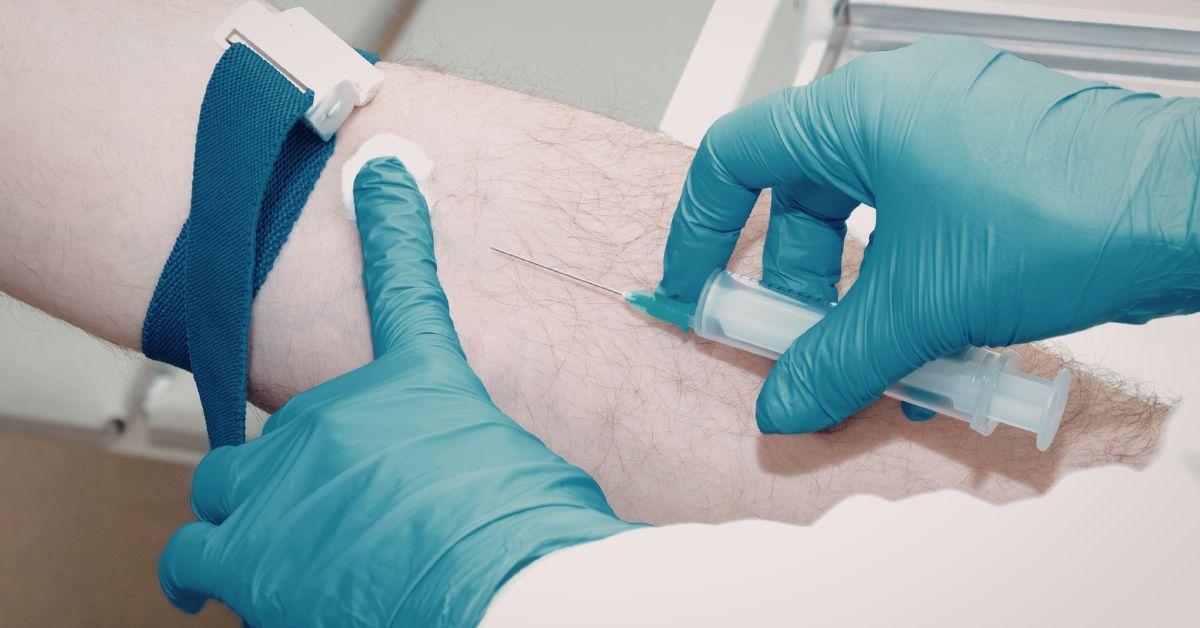
Evacuated tube systems are the gold standard for routine venipuncture, but clinical reality frequently demands otherwise. Patients with difficult venous access, pediatric draws, peripheral IV line collections, and certain point-of-care settings all require a syringe-based approach followed by manual transfer of the sample into collection tubes. This step carries well-documented risks—both to healthcare workers and to the integrity of the specimens being collected.
Blood collection is one of the most frequently performed clinical procedures across hospitals, diagnostic laboratories, outpatient clinics, and mobile healthcare services. Despite being routine, venipuncture remains highly technique-sensitive. Small procedural errors can compromise specimen quality, delay diagnosis, and require costly redraws.
A culture of safety in blood collection is not a slogan on a poster or a line in a compliance manual. It is the set of everyday behaviors, decisions, and tools that protect patients and healthcare workers from avoidable harm. Policies matter, but culture determines whether those policies are followed when the room is busy, the patient is anxious, and the schedule is tight.
Medical devices used in daily healthcare, such as blood collection needles and safety sets, are only as effective as their usability at the front lines. Bridging the gap between user input and product design is crucial in healthcare. The pechange the meta descriptions for the list of blogs I shared with youople who use devices every day have invaluable insights into what works and what doesn’t.
Blood collection devices may appear simple on the surface, but their design is the product of countless clinical decisions, real-world constraints, and safety considerations. Behind every grip texture, visual cue, and activation mechanism is a deliberate process aimed at reducing errors, improving first-stick success, and protecting both patients and clinicians.
Blood collection devices sit at the intersection of patient safety, occupational health, and diagnostic accuracy. As regulatory expectations continue to evolve, laboratories and healthcare facilities must ensure that the devices they use are not only clinically effective, but also fully compliant with U.S. and applicable global standards. In 2026, regulators are placing increased emphasis on risk management, labeling clarity, material safety, and post-market oversight — making regulatory literacy a practical necessity, not just a procurement concern.
Difficult blood draws are an unavoidable reality in clinical practice. Small or rolling veins, dehydration, pediatric patients, and chronic illness all increase the likelihood of failed venipuncture attempts. When first-stick success drops, the consequences extend beyond patient discomfort — delays in diagnosis, compromised sample quality, increased sharps exposure, and staff frustration quickly follow.