


Press Enter to search

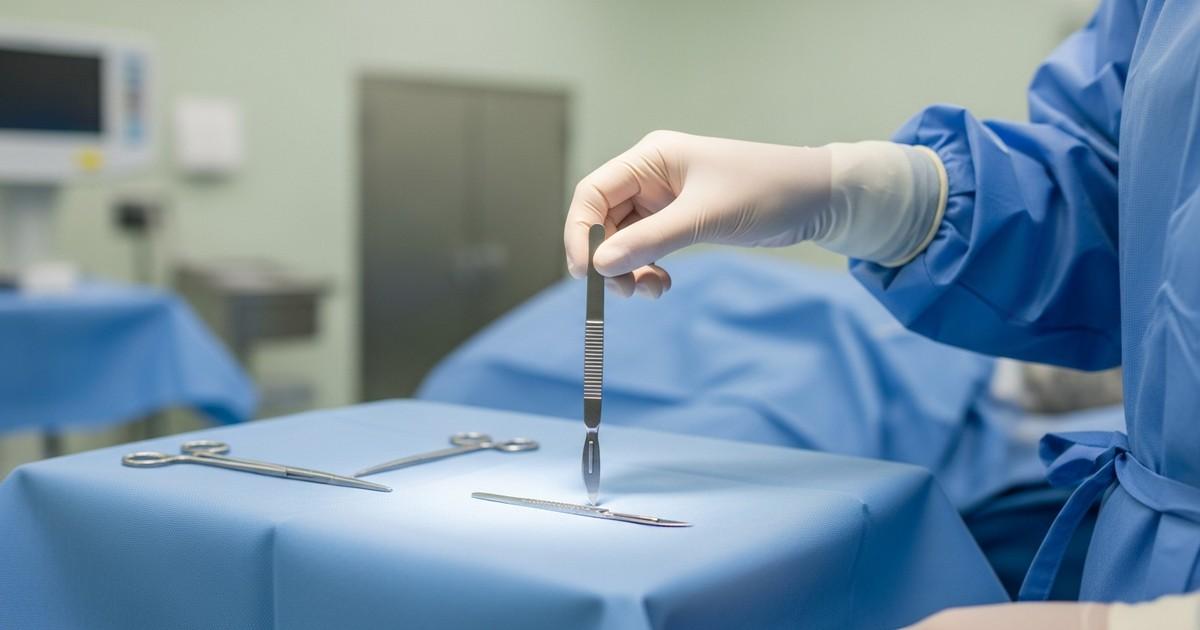
In operating rooms and sterile processing departments, scalpels are among the most hazardous instruments to handle — not during incision, but during passing, blade removal, and disposal. According to Exposure Prevention Information Network (EPINet) data summarized by the CDC, scalpel blades account for approximately 6–8% of all sharps injuries across hospital settings — and a 2023 report from the National Institute for Occupational Safety and Health (NIOSH) found that OR sharps injuries actually increased over time, even as nonsurgical sharps injuries declined. The problem is not technology — it is training, workflow, and compliance.
EPINet data identify three phases where scalpel injuries concentrate:
The primary federal standard is OSHA's Bloodborne Pathogens Standard, 29 CFR 1910.1030. Key requirements for scalpel handling:
The Needlestick Safety and Prevention Act requires employers to evaluate and deploy safety-engineered devices and involve frontline staff in device selection. Yet Massachusetts sharps injury surveillance data show that, as of the most recent 2021–2022 reporting period, 42% of injuries still involve devices without safety features — a persistent gap between policy and practice. See OSHA Compliance in Medico-Surgical Settings for a broader look at building a compliant environment.
The neutral zone is a designated area — a Mayo stand, magnetic pad, or basin — where one team member places a sharp and another retrieves it, without both hands present simultaneously. AORN recommends establishing it during the preoperative briefing for every case, with a verbal announcement each time a sharp is placed. The rule is simple: only one person handles a sharp at a time.
For laparoscopic and robotic cases where the surgeon cannot look away from the monitor, a partial technique applies — direct handoff to the surgeon, return via the neutral zone. Monitoring neutral zone adherence by service line identifies where coaching is needed most.
Blade removal is the highest-risk step in instrument reprocessing. Options that comply with OSHA:
For disposal, the sharps container must be within arm's reach at the point of use. Never carry an unsheathed blade across the room. Never place a blade in general waste. Replace containers before they reach the fill line — walking past a full container is how downstream workers get hurt.
Safety-engineered scalpels with retractable or shielded blades reduce exposure risk during passing and disposal. However, a systematic review in BMJ Open found insufficient evidence to support safety scalpels as a standalone intervention. They work best as part of a comprehensive program — alongside neutral zones, blade removers, double gloving, and blunt suture needles — not as a replacement for it. A hospital-based implementation study found modest but measurable injury reductions after safety-engineered device adoption, with the greatest benefit among nurses. For a detailed comparison, see Safety Scalpels vs. Traditional Scalpels.
Access drives compliance more than attitude. A study of home care nurses found that when safety devices were consistently provided, 95% of staff used them on the most recent procedure. When devices were not reliably stocked, that dropped to 15–50% — and 60–80% of non-users said the device simply was not available. Procurement and supply chain are compliance issues, not just training issues.
A dermatologic surgery study found nearly four times the risk of a sharps injury during Mohs procedures when the surgical assistant was untrained. Training must reach every person who touches a scalpel — not just surgeons. The CDC Sharps Injury Prevention Program Workbook provides a structured framework: baseline injury data, role-specific training, near-miss reporting, and frontline involvement in device selection. Culture and leadership modeling complete the picture — when charge nurses and OR directors visibly enforce neutral zones, the behavior normalizes across the team.
MYCO Medical offers engineering controls for each high-risk phase of scalpel use.
RELI®-CUT Disposable Retractable Safety Scalpels with TECHNOCUT® Premium Blade — top-activated retractable blade with audible position confirmation and a final lock for safe handling and disposal. Available in sizes #10, #11, #12, #15, and #20.
REDI-CUT® Disposable Safety Scalpel with TECHNOCUT® Premium Blade and Retractable Sheath — audible clicks confirm Safe, Ready to Use, and Final Lock positions. Blade can be covered for safe passing in the neutral zone. Available in sizes #10, #11, and #15.
TECHNOCUT® PRO Cartridge Blade Management System — attaches to most ISO 7740-compliant handles. Protective sliding sheath enables one-handed blade removal and disposal while keeping fingers clear of the cutting edge. Meets OSHA Bloodborne Pathogens and Needlestick Prevention guidelines.
QLICKSMART® BladeFLASK — puncture-proof, OSHA-compliant disposal system. Single-handed activation captures blades without direct contact. Built-in counter with automatic shut-off when full.
Browse the full MYCO Medical Blades & Scalpels portfolio, or contact our team to discuss the right solution for your facility.
What percentage of sharps injuries are caused by scalpels?
EPINet surveillance data summarized by the CDC show scalpel blades account for approximately 6–8% of all sharps injuries across hospital settings. The true figure is likely higher — per the same EPINet/CDC data, roughly half of all sharps injuries go unreported.
Does OSHA require mechanical blade removers?
OSHA's Bloodborne Pathogens Standard prohibits manual removal of contaminated sharps. When blade removal from a reusable handle is necessary, it must use a mechanical device or one-handed technique. A 2005 OSHA interpretation letter explicitly confirms that a single-handed blade remover satisfies this requirement.
What is the neutral zone and who requires it?
The neutral zone is a designated area — Mayo stand, magnetic pad, or basin — where sharps are placed and retrieved without direct hand-to-hand transfer, ensuring only one team member handles a sharp at a time. AORN recommends integrating it into preoperative briefings for every procedure.
Are safety scalpels proven to reduce injuries on their own?
A BMJ Open systematic review found insufficient evidence to support safety scalpels as a standalone intervention. They are most effective as part of a broader program that also includes neutral zones, blade removers, double gloving, and proper disposal.
Why do compliance rates vary so much between facilities?
Device availability is the primary driver. A study of home care nurses found that when safety devices are consistently provided, 95% of staff use them. When not reliably stocked, compliance falls to 15–50%. Procurement and supply chain gaps are compliance problems, not just training problems.
Who is at risk from improperly disposed scalpels?
Per EPINet/CDC surveillance data, approximately 25% of all sharps injuries occur to downstream non-users — waste handlers, environmental services staff, and laundry workers. Proper point-of-use disposal in puncture-resistant containers, replaced before the fill line, protects everyone downstream.


