Press Enter to search

Few device choices in anesthesia and diagnostic medicine carry as much day-to-day consequence as the spinal needle. Tip geometry and gauge influence how easily the needle is placed, how clearly cerebrospinal fluid (CSF) confirms position, and how likely the patient is to develop a post-dural puncture headache (PDPH) — a complication that can extend a hospital stay or bring a discharged patient back through the door.
Needle selection is also one of the best-studied questions in regional anesthesia, which means clinical and procurement teams do not have to rely on habit. This guide covers the two major spinal needle tip designs, how gauge and length affect performance, how color coding works, and where epidural needles fit.
Spinal needles fall into two families, distinguished by how the tip passes through the dura.
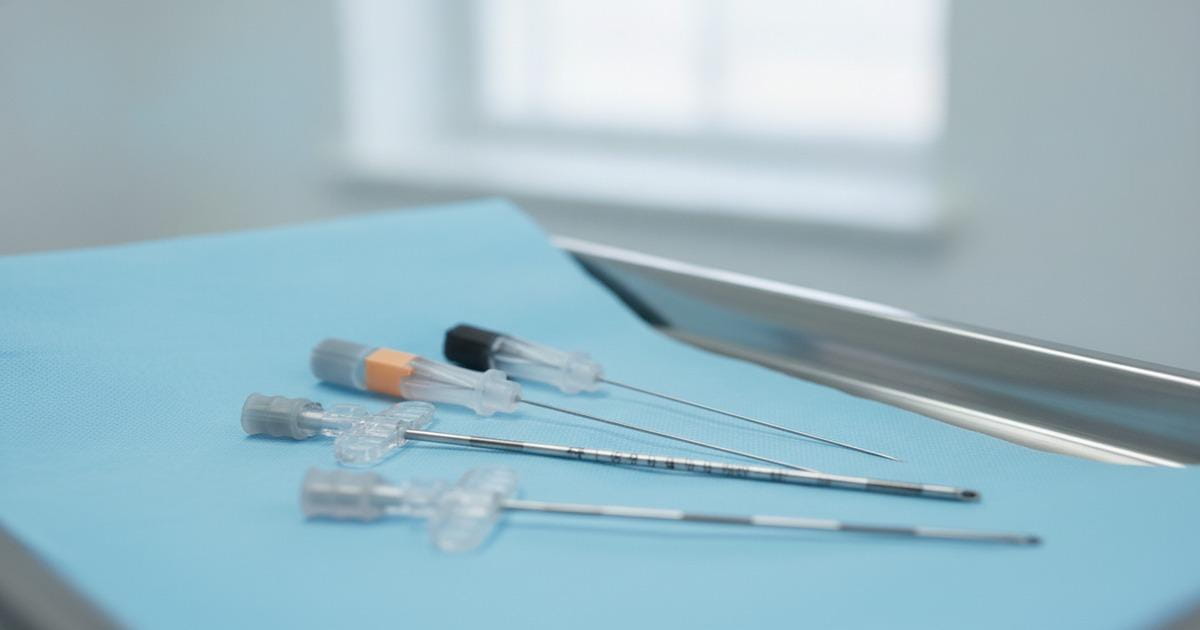
Quincke needles have a sharp cutting bevel that slices through dural fibers. The design offers a familiar feel, efficient insertion, and rapid CSF return. The RELI® Quincke Point Spinal Needle is manufactured with computerized grinding for sharp, consistent needle quality, an exact fit between stylet and cannula bevel designed to minimize coring and trauma, and large, clear hubs for enhanced tactile feel and visualization of CSF. Smooth insertion resistance helps clinicians identify tissue layers as the needle advances.
Pencil point needles (often called atraumatic needles, and available in Whitacre and Sprotte styles) have a solid, rounded tip with a side port just behind it. Rather than cutting the dura, the tip is designed to spread its fibers, leaving a smaller defect that closes more readily. The RELI® Pencil Point Spinal Needle pairs an atraumatic point with side-port dispensing, designed to greatly reduce loss of CSF and support patient comfort and recovery.
PDPH develops when CSF continues to leak through the puncture site after the procedure, lowering intracranial pressure and producing a positional headache. Needle design directly affects that risk.
The largest analysis to date, a 2018 meta-analysis published in The Lancet, pooled 110 randomized trials covering more than 31,000 patients. PDPH occurred in 4.2% of patients with atraumatic needles versus 11.0% with conventional cutting needles — with no significant difference in first-attempt success (86% vs. 88%) or overall failure rate. Based on that evidence, a BMJ Rapid Recommendation clinical practice guideline advises using atraumatic needles for lumbar punctures.
Head-to-head comparisons at the same gauge point the same way. In a randomized study of 676 outpatients receiving spinal anesthesia with 27-gauge needles, PDPH occurred in 2.70% of the Quincke group versus 0.37% of the Whitacre group.
Gauge matters as well, particularly for cutting needles. A randomized comparison in 480 cesarean patients reported PDPH in 8.3% with a 25-gauge Quincke, 3.8% with a 27-gauge Quincke, and 2.0% with a 27-gauge Whitacre — smaller diameter helped, and the pencil point design helped further.
None of this makes the Quincke design obsolete. Many clinicians prefer a cutting bevel where tactile feedback, stiffness, or rapid CSF return is the priority — for example, in patients with difficult anatomy — and diagnostic lumbar punctures often call for a larger bore. The practical takeaway for most facilities is to stock both designs and match the needle to the case.
Adult spinal needles typically range from 22 to 27 gauge. Finer needles (25G–27G) are common for spinal anesthesia because they are associated with lower PDPH rates, while a 22G needle remains useful when stiffness, tactile feedback, or faster CSF return matters more. The standard adult length is 3.5 inches (approximately 90 mm), with longer needles available for patients with deeper anatomy.
Needle hubs are color coded by gauge under International Organization for Standardization (ISO) 6009, a standard recognized by the U.S. Food and Drug Administration: for example, 22G is black, 25G is orange, and 27G is medium grey. Color helps speed identification at the point of use, but purchasing specifications should always name the gauge, length, and tip style rather than relying on hub color alone. For a deeper look at gauge identification, see our guide to needle gauge color coding and ISO standards.
Epidural anesthesia works differently — the needle is meant to stop short of the dura, so the design priorities change. The Tuohy needle uses a curved, non-coring tip that directs a catheter into the epidural space, and adult sizes typically run 17 to 18 gauge at about 9 cm with centimeter depth markings. Those markings are not decorative: as the New York School of Regional Anesthesia (NYSORA) explains, the loss-of-resistance technique identifies when the needle enters the epidural space, and the depth markings tell the clinician how deep that space sits — the measurement that determines how far to thread and where to secure the catheter.
The RELI® Tuohy Point Epidural Needle, Integrated Wing features precision point-grinding for comfort and non-coring performance, wide metric marks for maximum visibility and accuracy, a large, clear hub for enhanced tactile feel, and color-coded stylet caps. It is available with a plastic or metal stylet, with integrated or detachable wings. For a broader discussion of complications and how needle choice affects them, see our article on the risks of neuraxial anesthesia.
For teams standardizing their spinal and epidural needle formulary, a short checklist covers most decisions:
MYCO Medical's RELI® anesthesia portfolio includes Quincke point spinal needles (with short bevel and metric marking variants), pencil point spinal needles, and Tuohy point epidural needles — all made of medical grade stainless steel and available in sterile and non-sterile packaging. Browse the full Needles & Syringes line, and contact our team to request evaluation samples or pricing for your facility.
What is the difference between a Quincke and a pencil point spinal needle?
A Quincke needle has a sharp cutting bevel that slices through dural fibers, while a pencil point needle has a rounded, atraumatic tip with a side port that spreads the fibers instead. The smaller dural defect left by a pencil point tip is associated with substantially lower rates of post-dural puncture headache.
Which spinal needle gauge is used for spinal anesthesia?
Most adult spinal anesthesia is performed with 25- to 27-gauge needles, which balance reliable performance with lower headache risk. A 22-gauge needle is often chosen when stiffness, tactile feedback, or faster CSF return is the priority.
Do pencil point needles make the procedure harder to perform?
The evidence says no. In the 2018 Lancet meta-analysis of 110 trials, first-attempt success rates were statistically comparable between atraumatic and conventional needles, and overall failure rates did not differ significantly.
What causes a post-dural puncture headache?
PDPH results from CSF continuing to leak through the dural puncture site, which lowers pressure around the brain and produces a headache that worsens when upright. Larger punctures and cutting-tip needles leave defects that leak more, which is why finer gauges and pencil point tips are associated with lower risk.
What size is a Tuohy epidural needle?
Adult Tuohy needles are typically 17 or 18 gauge and about 9 cm long, with markings at 1-cm intervals. The markings let the clinician read the depth of the epidural space and place the catheter accordingly.
How are spinal needle gauges color coded?
Needle hub colors follow the ISO 6009 standard — for example, black for 22G, deep blue for 23G, orange for 25G, and medium grey for 27G. Always confirm the printed gauge on the packaging as well; color is an identification aid, not a substitute for the label.